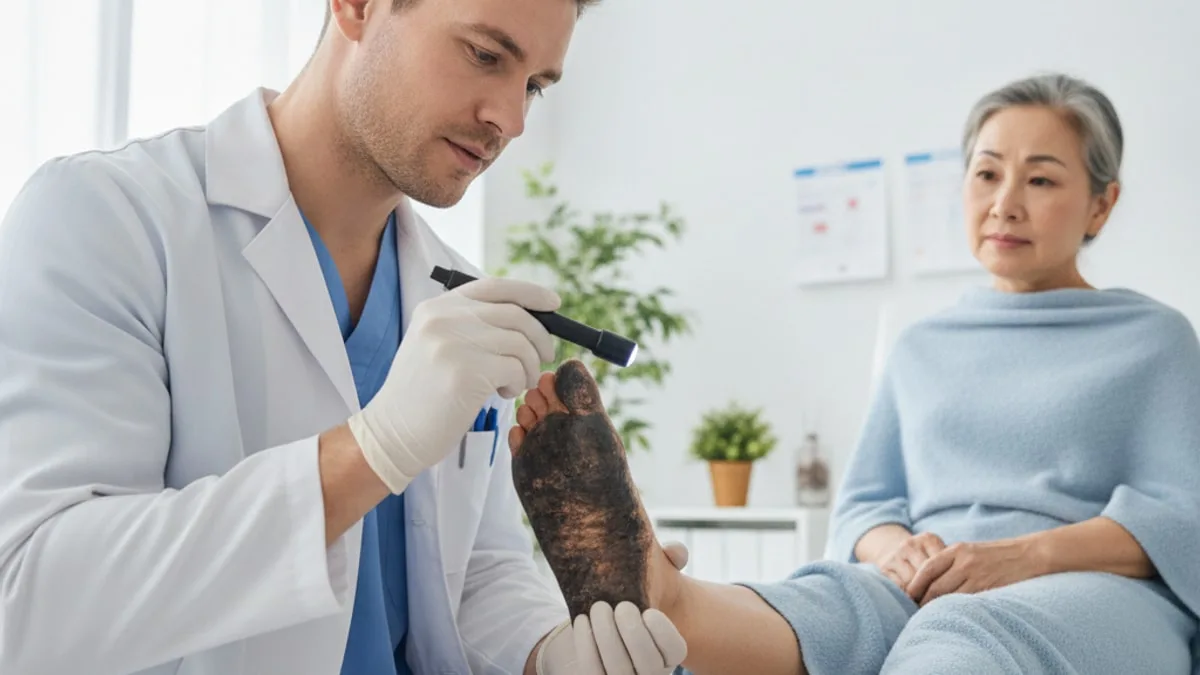
Gangrene Signs: Dry, Wet and Gas Gangrene
Foot pain that spreads fast and feels far worse than the skin looks, fever or chills, dark blistering skin, or skin that crackles under the fingers all need emergency care now, so call 911 or go to the emergency department.
A clinician interprets those results alongside a hands on look at the foot. This page explains the three patterns people describe as dry, wet and gas, the everyday situations that lead into them, and the markers worth checking when a foot wound is not behaving.
What usually causes tissue death in the feet?
Foot tissue dies when the blood carrying oxygen to it is cut off, or when an infection destroys tissue faster than the body can defend it, and the trigger is usually an ordinary event rather than a lab finding.
The everyday starting points are familiar ones. Shoes that rub and raise a blister nobody notices. A small cut from trimming a nail. A burn from hot water, a heater or hot pavement in a foot that has lost some feeling. Cold injury after hours outdoors. A dressing, sock or boot tight enough to squeeze circulation. Long stretches of pressure on one spot during illness or reduced mobility. Smoking and nicotine, which narrow blood vessels. Heavy alcohol use, which dulls sensation and makes an injury easier to shrug off. Short sleep and high stress, which make it easier to skip the daily foot check. Older age, which often brings stiffer arteries and thinner skin. Some medicines also change how skin breaks down or how the body responds to infection, and your prescriber is the right person to ask about yours.
Two underlying problems matter a great deal here. Long standing high blood sugar can damage the small nerves and vessels of the foot, so an injury is neither felt at the time nor supplied well enough to heal. Narrowed leg arteries reduce the blood reaching the toes, which is why the toes are often the first area to change color.
People describe three broad patterns, and they do not behave the same way.
| Pattern | What it tends to look and feel like | What tends to sit behind it |
|---|---|---|
| Dry | Skin turns dusky, brown or black, dries out and shrinks, often with a fairly sharp border. The foot is frequently cool and numb. There is usually little pus and little smell, and it develops over days to weeks. | Gradual loss of arterial blood flow, often alongside long standing nerve damage. |
| Wet | Swelling, blistering, weeping fluid, a foul smell and spreading redness, often with fever and heavy pain. It moves faster than the dry pattern. | Infection taking hold in tissue that was already injured or poorly supplied with blood. |
| Gas | Severe pain that outpaces anything visible on the skin, fast swelling, dusky or bronze discoloration, and a crackling feel under the skin from gas inside the tissue. Hours matter. | Gas forming bacteria entering through a wound, which is a surgical emergency. |
Research suggests that necrotizing soft tissue infections, the group behind the fastest moving pattern, are uncommon but carry a high risk of organ failure and death, so immediate surgical assessment takes priority over waiting for results 1. A review of necrotizing fasciitis describes pain out of proportion to the visible skin changes, skin discoloration, blistering and rapid whole body illness as the findings that should trigger emergency assessment 2. Crepitus, the crackling of gas under the skin, is described as a late finding rather than an early warning 3. Studies suggest that a shorter time from arrival to the first operation is associated with lower mortality in necrotizing soft tissue infections 4.
Which blood tests can help explain it?
No blood test can confirm that tissue has died, but a short list of routine markers tells a clinician how the body is coping and which underlying problems are in play.
| Marker | Why it is linked to this symptom | What a result can and cannot tell you |
|---|---|---|
| Total WBCs | White cells rise when the immune system responds to infection, and white cell count is one of the routine tests built into scoring described for early recognition of necrotizing fasciitis 5. | Shows that the immune system is activated. It cannot say where the problem is, which organism is involved, or how deep the damage goes, and it can look unremarkable early on. |
| Fasting Glucose | Blood sugar after an overnight fast reflects how well glucose is being handled. | Gives a single snapshot. It cannot show how long sugar has been running high, and it moves with acute illness, stress and the length of the fast. |
| Hemoglobin A1C | A1C estimates average blood glucose across roughly the past three months. | Describes glucose control over time. It says nothing about circulation in the foot and can read falsely low or high when red blood cell turnover is unusual. |
| Creatinine | Creatinine reflects how well the kidneys are filtering, kidney function is part of how severity is graded in necrotizing soft tissue infections 1, and it appears in the same routine scoring 5. | Flags a change in filtration. It cannot separate dehydration from kidney injury on its own, and it shifts with muscle mass and heavy training. |
Reference ranges vary by lab, age and sex, so read every number against the range as printed on your lab report.
Can a high white cell count mean an infection in the foot?
A high white cell count means the immune system is responding to something, and it never says by itself where that something is. White cells are the circulating arm of the immune defence, and their numbers climb when bacteria breach the skin barrier, which is why the count is checked when a foot wound looks angry or a toe changes color.
Research suggests that scoring systems built from routine blood tests, white cell count among them, can support earlier recognition of necrotizing fasciitis but should not be used to rule it out when the clinical picture is worrying 5. That is the practical point. A reassuring count does not cancel out a foot that hurts out of proportion, and a high count does not localise the problem to the foot.
Plenty of ordinary things move this marker. A chest or urinary infection somewhere else entirely. Hard training in the previous day or two. Acute stress. Smoking. Recovery from a recent illness. Some medicines raise or lower the count, which is another question for your prescriber. A persistently unusual Total WBCs result is worth discussing with a clinician rather than interpreting alone, especially alongside a wound that is not closing.
Research suggests that the organisms involved in necrotizing fasciitis and the tools used to recognise it have shifted over time, and that imaging and scoring support clinical judgement rather than replace it 7.
Does fasting glucose change how a foot wound heals?
Fasting glucose shows where blood sugar sits after an overnight fast, and it is one of the first markers a clinician looks at when a foot wound heals slowly or a toe darkens. Sustained high blood sugar damages the smallest blood vessels and the nerves that run to the feet. Less sensation means a blister or a stone in a shoe goes unnoticed for days. Less small vessel supply means the tissue that was injured has fewer resources to repair itself and less capacity to fight off bacteria.
Research suggests that diabetes is among the underlying conditions most frequently reported in people with necrotizing soft tissue infections across pooled international data 6. Glucose also appears inside the routine laboratory scoring described for early recognition of necrotizing fasciitis 5, which reflects how closely sugar handling and severe soft tissue infection travel together.
One reading is only one reading. A Fasting Glucose value moves with acute illness, a poor night of sleep, significant stress, a fast that was shorter than it should have been, and some medicines. The useful approach is observation, then meaning, then a conversation. A single raised value is one possible signal that glucose handling deserves a closer look, not a conclusion about any condition.
What does hemoglobin A1C add that one glucose reading cannot?
A1C estimates average blood glucose over roughly the past three months, so it smooths out the day to day noise that a single fasting value carries. It works because glucose attaches to hemoglobin inside red blood cells, and those cells live long enough to record a running average.
That longer view matters for the feet specifically. Nerve and small vessel changes build up over years of elevated sugar rather than over one bad week, which is why a clinician reviewing a slow healing foot wound often wants the average rather than the snapshot. Research suggests that the comorbidity profile of people who develop necrotizing soft tissue infections is dominated by chronic conditions including diabetes 6, and studies suggest that recognising those underlying conditions early is part of how clinicians assess risk in necrotizing fasciitis 7.
A1C has real limits. Anything that changes red blood cell lifespan will shift it, including anemia, recent blood loss, a transfusion, some inherited hemoglobin variants and advanced kidney disease. In those situations a Hemoglobin A1C result can read lower or higher than the person's true average, so it is interpreted next to glucose and the clinical picture rather than on its own.
Why would a clinician check creatinine for a foot problem?
Creatinine is checked because it reports on the kidneys, and the kidneys are one of the first organs to show strain when a serious infection spreads beyond the skin. Creatinine is a waste product of normal muscle turnover that the kidneys filter out, so a rising value suggests filtration has dropped.
In severe soft tissue infection, blood pressure falls, fluid shifts and the kidneys receive less flow, which is part of why organ function sits at the centre of how clinicians grade severity in necrotizing soft tissue infections 1. Creatinine is also one of the routine tests included in the laboratory scoring described for early recognition of necrotizing fasciitis 5. Kidney function has a second, quieter relevance. Reduced kidney function often travels with the same vascular changes that reduce blood flow to the feet.
Ordinary things move this marker too. A heavy lifting session, a high protein meal, dehydration, and higher than average muscle mass all nudge creatinine upward without any kidney problem. Some medicines shift it as well, which your prescriber can explain. A Creatinine result that sits outside the range on your report is worth discussing with a clinician promptly rather than watched quietly, particularly alongside a foot wound.
What can a normal panel still miss?
A completely normal blood panel can sit alongside a foot that is in serious trouble, which is the single most important limit to understand here. Blood tests measure what is circulating. They do not measure blood flow into a toe, the depth of a wound, pressure under a callus or the state of tissue beneath intact looking skin.
Several causes never show up in bloodwork at all. Narrowed arteries are assessed with pulse examination, blood pressure comparisons between ankle and arm, and imaging. Loss of protective sensation is assessed by testing the foot directly and sometimes with nerve conduction tests. Pressure damage from footwear or immobility is found by looking. Early infection under the skin can be quiet in the blood and loud on examination.
Research suggests that laboratory scoring for necrotizing fasciitis lacks the sensitivity to exclude the condition, so a low score should never delay surgical assessment of a suspicious limb 5, and studies suggest that time to that first operation is one of the strongest levers on outcome 4. Studies also suggest that the organisms responsible and the outcomes observed differ between world regions, so local patterns shape what clinicians expect 8.
The honest summary is that labs describe context and risk. Examination, imaging and, when the picture is severe, direct surgical inspection describe the foot.
When should you see a clinician quickly?
Some foot findings are emergencies and should not wait for an appointment, a phone triage line or the morning. Call 911 or go to the emergency department now if any of the following are present.
- Pain in the foot or leg that is far worse than the skin appearance suggests, or pain that is escalating by the hour
- Redness or swelling that is visibly spreading, with a line that advances while you watch
- Fever, shaking chills, feeling confused, a racing heart or feeling profoundly unwell alongside a foot wound
- Skin turning purple, grey, bronze or black, or blisters filling with dark or cloudy fluid
- A crackling or popping feel under the skin when it is pressed
- Foul smelling discharge from a foot wound
- A foot that has become suddenly cold, pale and numb
Those signs overlap heavily with the whole body response to severe infection, and the pattern of sepsis symptoms is worth recognising in advance. A review of necrotizing fasciitis frames early recognition and immediate surgical referral as the decisive steps 2, and research suggests that outcomes in these infections hinge on how quickly the first operation happens 4.
Other findings deserve a prompt clinician visit rather than an emergency one. A wound on the foot that has not improved in a week. New numbness or burning in the toes. Skin that stays broken under a callus. Recurrent blisters in the same spot. Any treatment decisions belong to a licensed provider who has examined the foot.
If you are having thoughts of self-harm, call or text 988 (US) or your local emergency number now.
How can you check these markers?
All four markers discussed here are measured on a standard blood draw, and the FitScript Essential panel includes white cell count, fasting glucose, hemoglobin A1C and creatinine in one sitting. Membership testing covers 150+ biomarkers tested per year, so these values can be tracked over time rather than read once and forgotten.
Results arrive with plain language interpretation from Atlas, the AI health advisor, which explains what each value describes and what it does not. A licensed clinician reviews the picture and decides on any next step, including whether an examination of the feet, vascular testing or referral is appropriate.
This article is educational and is not medical advice. Discuss your results and any treatment with a clinician or licensed provider who knows your history.
Key takeaways
- Gangrene in the feet means tissue has died, usually after arterial blood flow failed, after an injury went unnoticed in a numb foot, or after infection outran the body's defences.
- The dry pattern is slow, dark, dry and often numb. The wet pattern swells, weeps and smells. The gas pattern moves in hours and crackles under the skin.
- Spreading pain out of proportion to the skin, fever, dark blistering or crackling skin means calling 911 or going to the emergency department, not waiting on a test result.
- White cell count, fasting glucose, hemoglobin A1C and creatinine describe immune activation, glucose handling and kidney function, which together frame risk and severity.
- A normal panel does not exclude a serious foot problem, because blood tests cannot see circulation, sensation or tissue depth.
- Observation, then possible meaning, then a conversation with a clinician is the right sequence for any result outside the range on your report.
References
- Necrotizing Soft Tissue Infections: A Review. JAMA Surgery, 2024.
- Necrotizing fasciitis a review. Polski Przeglad Chirurgiczny, 2022.
- Necrotizing fasciitis: A comprehensive review. Nursing, 2020.
- Time is of the essence when treating necrotizing soft tissue infections: a systematic review and meta-analysis. World Journal of Emergency Surgery, 2020.
- Early diagnosis of necrotizing fasciitis. The British Journal of Surgery, 2014.
- Global patterns of necrotizing soft tissue infections: A systematic review and meta-analysis. Surgery, 2021.
- Necrotizing fasciitis: an update on epidemiology, diagnostic methods, and treatment. Current Opinion in Infectious Diseases, 2024.
- Regional Variations in Microbiology and Outcomes of Necrotizing Soft Tissue Infections: A Systematic Review and Meta-Analysis. Surgical Infections, 2022.
Common questions
What is toe gangrene?
Toe gangrene means tissue in one or more toes has died, usually after blood flow to the smallest vessels failed or after an infection took hold in an injured toe. The toe darkens to brown, purple or black and may feel cold or numb.
What is gas gangrene?
Gas gangrene is tissue death caused by gas forming bacteria that enter through a wound and spread through muscle and soft tissue within hours. The skin may look bronze or dusky, swelling comes on fast, pain is severe, and pressing the skin can feel like crackling. This is an emergency, so call 911 or go to the emergency department.
What is wet gangrene?
Wet gangrene is tissue death that happens alongside active infection, so the area swells, blisters, weeps fluid and often smells foul while redness spreads outward. Fever and heavy pain are common, and it progresses faster than the dry pattern. Anyone with these signs should call 911 or go to the emergency department rather than wait.
How is dry gangrene different from wet gangrene?
Dry gangrene develops slowly when arterial blood flow fades, leaving skin that is dark, dry, shrunken and often numb with little pus or smell. Wet gangrene involves infection, so the area is swollen, moist, foul smelling and painful, and it spreads quickly.
Does tissue affected by gangrene recover?
Tissue that has already died does not come back. Care focuses on restoring blood supply where possible, controlling infection and removing dead tissue, and the surrounding healthy tissue can heal once those things are addressed. A licensed provider decides what is appropriate after examining the foot and reviewing imaging and bloodwork.
What does a high white blood cell count mean with a foot wound?
It means the immune system is reacting to something, which may or may not be the foot. The count cannot show where the infection is, how deep it goes, or which organism is involved. A normal count also does not rule out a serious problem, so the foot examination matters more than the number.
Does diabetes raise the risk of foot problems like this?
In people with diabetes, long standing high blood sugar can reduce sensation in the feet and damage the small vessels that supply skin, so an injury is easier to miss and slower to heal. Daily foot checks and well fitting footwear help. A clinician should review any wound that is not improving.
Which blood tests are worth checking for a slow healing foot wound?
White cell count, fasting glucose, hemoglobin A1C and creatinine are the usual starting set, because they describe immune activation, glucose handling over the short and long term, and kidney function. They give context rather than a diagnosis. A clinician reads them alongside an examination of the foot and circulation testing.