Viral vs Bacterial Infection: Signs, Tests, Why It Matters
Trouble breathing, confusion, a stiff neck with fever, or a spreading rash that does not fade when pressed means call 911 or go to the emergency department.
The rest of this page covers what each of those markers reflects, what a result can and cannot tell you, and where a blood panel runs out of road.
What is actually behind an illness like this?
Both viruses and bacteria are germs, yet they are built differently and behave differently once inside the body, and plenty of run-down days are not infections at all.
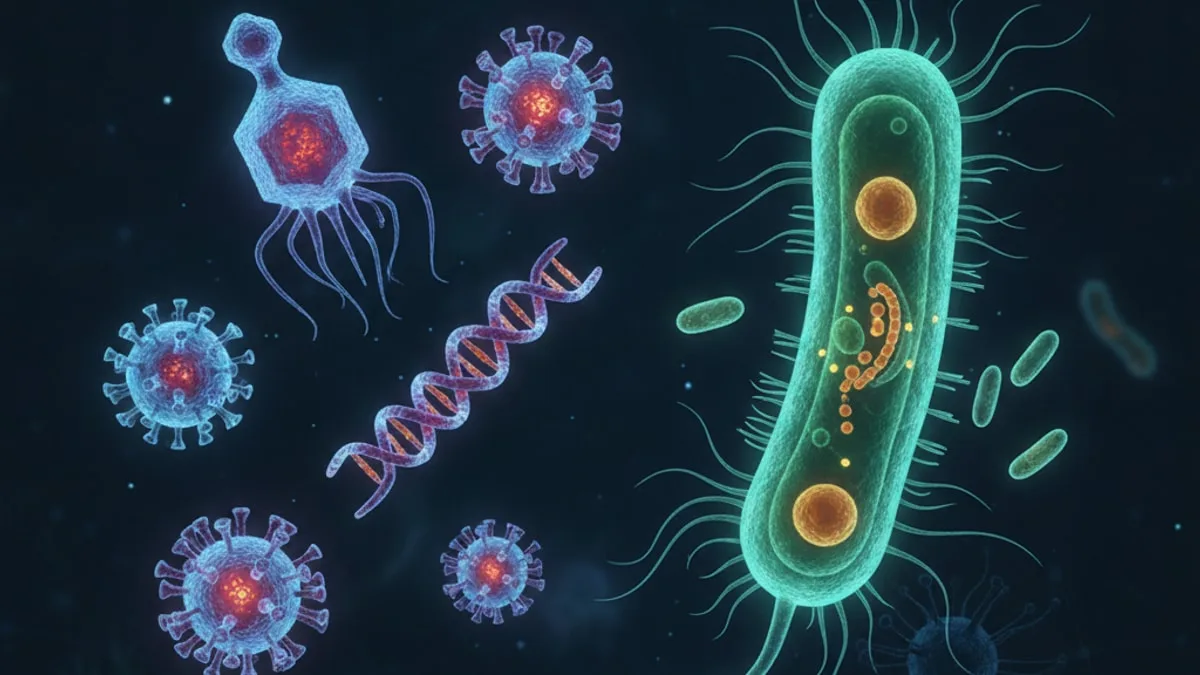
A bacterium is a complete single cell. It takes in nutrients, copies its own DNA and divides on its own, whether that is on skin, in the gut or in tissue where it does not belong. A virus is far smaller and is not a cell. It is genetic material wrapped in a protein coat, and it has to get inside one of your own cells and borrow that cell's machinery to make copies of itself. The immune system answers those two threats with overlapping but not identical responses, which is the reason a blood count can lean one way or the other.
That difference matters at the point of care, because treatment from a clinician differs for each type. Some medicines act on bacteria and do nothing against a virus, and whether any medicine fits a given illness is a judgement a licensed provider makes after reviewing the person. Treatment decisions belong to a licensed provider.
Before an infection is assumed, it is worth naming the everyday states that feel like the start of one. Short sleep across several nights leaves people achy and foggy. A hard training block, a stressful stretch at work, under-eating, low fluid intake and alcohol can all produce heavy limbs and a dull head. Seasonal allergies can mimic the first days of a cold with a blocked nose and a scratchy throat. Some medicines can cause tiredness or a dry cough, and that is a question for your prescriber. Life stage shifts things too, because sleep quality, hormones and recovery capacity all change with age. Many of those states never show up as a lab finding.
Research suggests that history and examination findings on their own leave a wide grey zone between bacterial and viral illness 1. The colour of mucus is the clue people trust more than it deserves, and one systematic review found no evidence that symptom duration or purulent nasal discharge separates bacterial from viral acute sinus inflammation 2.
Which blood tests can help tell them apart?
The complete blood count with differential is the starting point, and three of its parts get the closest look here. Those are the total white cell count, the absolute neutrophil count and the absolute lymphocyte count.
| Marker | Why it is linked to this symptom | What a result can and cannot tell you |
|---|---|---|
| Total WBCs | The total white cell count moves as the bone marrow responds to an infection and as cells leave the bloodstream for tissue. | It can show that the immune system is responding, and it cannot name the germ or settle whether the cause is viral or bacterial. |
| Neutrophils Absolute | Neutrophils are the fast responders that travel toward bacteria and damaged tissue. | A shift can support a bacterial picture when it fits the examination, and it also moves with physical stress, injury and inflammation of other kinds. |
| Lymphocytes Absolute | Lymphocytes deal with virus-infected cells and build immune memory, so a viral illness can change their numbers. | A change can fit a viral process, and it cannot confirm one, because stress hormones, recent illness and age move the count as well. |
Compare each value against the range as printed on your lab report, because reference ranges differ by laboratory, by age and by sex. A value outside the printed range is worth discussing with a clinician, who decides what it reflects.
Two further host-response tests sit alongside the blood count and are reported in words here rather than numbers, because the thresholds belong to the ordering clinician. The first is C-reactive protein, a protein the liver releases when inflammation rises. Research suggests that C-reactive protein measured during acute undifferentiated fever separates bacterial from viral causes better than chance, with enough overlap that a single value is hard to act on by itself 3. The second is procalcitonin. A systematic review and meta-analysis reported that procalcitonin alone does not reliably distinguish bacterial from viral pneumonia 4.
Can a high white cell count point to a bacterial infection?
It can point that way, and it cannot settle the question on its own.
White blood cells are the circulating arm of the immune system. During an acute infection the marrow can release more of them, and they can also drain out of the bloodstream into infected tissue, so the total count can rise, fall or stay put depending on the germ, the timing and the person. That is why one number read in isolation is weak. The differential, which splits the total into its cell types, carries far more information than the headline figure.
Research suggests that no single routine blood marker, the white cell count included, separates bacterial from viral infection cleanly 5. A literature review of blood markers in pneumonia reached a similar place, with individual markers overlapping between viral and bacterial causes 6.
Plenty of things besides infection move the count. Hard exercise in the hours before a draw, acute physical or emotional stress, smoking, pregnancy and some medicines can all shift it, and your prescriber is the person to ask about a medicine you take. Time of day plays a small part too. If you want to see what the marker covers in more depth, the Total WBCs page sets it out.
What do neutrophils show while you are fighting something off?
Neutrophils are the white cells that reach a site of bacterial invasion first, and their absolute count is one of the more informative parts of the differential.
They are short-lived cells built for speed. They engulf bacteria, release enzymes and then die, which is what gives pus its colour and thickness. A bacterial process in tissue can pull them out of the marrow in numbers, and immature forms can appear in the blood when the marrow is pushed hard.
The same cells carry information about how ill someone is, not only about which germ is involved. Research suggests that inflammatory markers measured early in acute bacterial and viral infection relate to how patients go on to fare 7. In suspected meningitis, blood and spinal fluid markers are used together with culture results to tell community-acquired bacterial and viral cases apart 8.
Other states move neutrophils without any germ involved. Intense training, a recent injury, surgery, smoking, chronic inflammation and some medicines all shift the number, and a prescriber can say whether something you take is relevant. The Neutrophils Absolute page covers the marker on its own terms.
Why do lymphocytes shift during a viral illness?
Lymphocytes are the cells that recognise virus-infected cells and build lasting immunity, so viral illness changes their numbers in ways a blood count can pick up.
This group includes T cells, B cells and natural killer cells. When a virus gets inside host cells, these are the cells that identify and clear them, and they are also the cells that remember the encounter. During an acute viral illness the circulating count can drop sharply as cells move into lymph nodes and tissue, and in other viral illnesses the count rises instead, sometimes with large reactive-looking cells on the smear. Both patterns are read against the clinical picture rather than alone.
Non-infectious influences matter here too. Acute stress and the hormone response that goes with it move lymphocyte numbers within hours, as does a hard training session shortly before a blood draw. Age changes the baseline, and so do some medicines, which is a conversation for your prescriber. The Lymphocytes Absolute page explains what the count tracks.
Does the answer change from a sore throat to pneumonia?
Yes, the usefulness of these tests depends on where in the body the illness sits and how ill the person is.
For pneumonia, both viral and bacterial causes occur, and mixed infection happens as well. Blood markers are used alongside a chest image and the examination, because reviews of those markers describe overlap between the two causes rather than a clean split 6, and procalcitonin by itself did not reliably distinguish them in a meta-analysis 4.
Bronchitis is inflammation of the airways below the throat, and it can follow a viral illness or involve bacteria. The cough can run on after other symptoms settle, which makes people assume the cause has changed when it has not. A clinician decides whether the picture needs imaging, swabs or bloods.
For sinus symptoms, the clues people reach for do not hold up, and the review named earlier found no evidence that how long symptoms last or how coloured the discharge is separates the two 2.
For suspected meningitis, the stakes change everything. A stiff neck with fever, severe headache with fever, confusion or a rash that does not fade under pressure means call 911 or go to the emergency department, and the separating work is done in hospital with spinal fluid, cultures and biomarkers together.
What can a normal panel still miss?
A complete blood count that sits inside the printed ranges does not rule out an infection, and several real situations produce exactly that result.
Timing is the first one. A panel drawn in the first hours of an illness can be taken before the host response has built, so the count catches the immune system mid-stride. A second draw later can look different.
Location is the second. An infection walled off in one place, a skin abscess or a contained urinary infection for instance, can produce little systemic signal while still needing care. A blood count also says nothing about which organism is present. That answer comes from a swab, a culture, a urine sample or imaging, ordered by a clinician.
Mixed pictures are the third. A viral illness followed by a bacterial one layered on top is a familiar sequence, and the blood count can blur the two. Non-infectious inflammation is the fourth, because autoimmune conditions, recent surgery and heavy training all move the same markers.
Research suggests that single markers perform less well than combinations, and that host-response measures are being read as groups rather than one at a time 5. Studies indicate that host biomarkers can be measured together to indicate whether an infection is viral or bacterial 9.
Finally, a panel does not measure how you feel. Lingering tiredness, poor sleep and reduced exercise tolerance after an illness are real and can sit on top of results that read as unremarkable.
When should you see a clinician quickly?
Some signs need emergency care, and others need a same-day call, and the two lists do not overlap.
Call 911 or go to the emergency department for any of these.
- Trouble breathing, or breathing that is fast and hard work
- Chest pain or pressure
- Fainting or passing out
- New confusion, or being very hard to wake
- A stiff neck with fever, or a severe headache with fever
- A rash that does not fade when a glass is pressed against it
- A seizure
- Lips, face or fingertips that look blue or grey
Contact a clinician the same day for any of these.
- A fever that keeps climbing or keeps coming back
- Feeling better and then clearly getting worse again
- A cough that is worsening rather than easing, or that brings up blood
- Back or side pain with fever
- Not keeping fluids down, or passing far less urine than normal
- Redness or swelling of the skin that is spreading
- Being unwell during pregnancy, which is a question for your OB or midwife, or a child who is unwell, which is a question for your child's pediatrician
- In people taking something that lowers immune defences, any new fever
No result on this page, and no symptom pattern, is a substitute for an examination. A clinician decides what any finding reflects and what care fits.
If you are having thoughts of self-harm, call or text 988 (US) or your local emergency number now.
How can you check these markers?
A complete blood count with differential is the single test that carries all three of these markers, and it is drawn from a standard blood sample.
The FitScript Essential panel measures the total white cell count together with the absolute neutrophil and absolute lymphocyte counts, so the three sit side by side on one report rather than being chased separately. FitScript's membership covers 150+ biomarkers tested per year, and Atlas, the AI health advisor, explains in plain language what each result shows and what it does not. A licensed clinician reviews the picture and decides on any next step, including whether any treatment is appropriate.
This page is educational and is not medical advice. Discuss your results and any treatment with a clinician or licensed provider.
If tiredness drags on well after the acute illness has passed, how long does fatigue last after illness walks through the timeline in more detail, and if the picture includes back or side pain with fever, kidney infection symptoms covers what that can look like.
Key takeaways
- Bacteria are complete cells that divide on their own, while viruses must enter your cells to copy themselves, and the immune response to each differs enough that blood tests can lean one way.
- Symptoms by themselves leave a wide grey zone, and mucus colour and symptom duration are weak separators 1, 2.
- The total white cell count, the absolute neutrophil count and the absolute lymphocyte count are the three parts of the blood count that carry the information, read together rather than one at a time.
- Host-response tests such as C-reactive protein and procalcitonin add context, and neither one settles the question alone 3, 4.
- A panel inside the printed ranges does not rule out infection, and it never names the organism.
- Trouble breathing, chest pain or pressure, fainting, confusion, a stiff neck with fever or a rash that does not fade under pressure means call 911 or go to the emergency department.
References
- Is it bacterial or viral? Criteria for distinguishing bacterial and viral infections. The Journal of Family Practice, 2008.
- No evidence for distinguishing bacterial from viral acute rhinosinusitis using symptom duration and purulent rhinorrhea: a systematic review of the evidence base. Otolaryngology Head and Neck Surgery, 2014.
- Value of C-reactive protein in differentiating viral from bacterial aetiologies in patients with non-malaria acute undifferentiated fever in tropical areas: a meta-analysis and individual patient data study. Transactions of the Royal Society of Tropical Medicine and Hygiene, 2021.
- Procalcitonin to Distinguish Viral From Bacterial Pneumonia: A Systematic Review and Meta-analysis. Clinical Infectious Diseases, 2020.
- Predicting Bacterial Versus Viral Infection, or None of the Above: Current and Future Prospects of Biomarkers. Clinics in Laboratory Medicine, 2019.
- Blood biomarkers differentiating viral versus bacterial pneumonia aetiology: a literature review. Italian Journal of Pediatrics, 2020.
- Inflammatory biomarkers to predict the prognosis of acute bacterial and viral infections. Journal of Critical Care, 2023.
- Distinguishing community-acquired bacterial and viral meningitis: Microbes and biomarkers. The Journal of Infection, 2024.
- Biosensors for detecting viral and bacterial infections using host biomarkers: a review. The Analyst, 2021.
Common questions
Is pneumonia viral or bacterial?
Pneumonia can be either, and sometimes both at once. The cause cannot be settled from how someone looks or sounds. A chest image, the white cell count with its differential and other host-response tests give a clinician the picture, and that clinician decides what the results reflect and what care is appropriate.
Is bronchitis viral or bacterial?
Bronchitis can be either. It is inflammation of the airways below the throat, and it can follow a viral illness or involve bacteria. The cough can run on after other symptoms settle, which does not by itself signal a change in cause. A clinician decides whether testing or any treatment is needed.
Can a blood test tell if an infection is viral or bacterial?
A blood test can shift the odds rather than give a verdict. The white cell count, the neutrophil count, the lymphocyte count and host-response proteins all overlap between the two. A clinician reads them alongside the examination, and a swab, culture or imaging is what identifies an organism.
What can a high white blood cell count point to?
A raised white cell count can point to the immune system responding to something, which may be an infection, inflammation, recent hard exercise, stress or a medicine effect. It does not name a cause. A value outside the range printed on your report is worth discussing with a clinician, who decides what it reflects.
What happens to lymphocytes during a viral illness?
Lymphocytes can fall as these cells leave the bloodstream for lymph nodes and infected tissue, and in other viral illnesses the count rises instead. Either pattern is read against the whole picture rather than on its own. Your clinician decides whether a repeat count or further testing is worth doing.
Does green mucus mean a bacterial infection?
No. The colour comes from enzymes released by immune cells in the mucus, and it appears in viral illness as well. Colour on its own does not separate the two. If symptoms are worsening or not easing, that is the reason to contact a clinician, not the shade of the mucus.
Is a sore throat viral or bacterial?
A sore throat can be either, and looking at the throat does not settle it. A clinician may take a throat swab when the examination suggests it is worth doing. Trouble breathing, trouble swallowing your own saliva or a muffled voice means call 911 or go to the emergency department.
When should I get blood tests for an infection?
A clinician decides when bloods add something, and that decision depends on how ill you are, where the symptoms sit and how long they have run. Testing very early can catch the immune response before it has built. If you are getting worse rather than better, contact a clinician the same day.