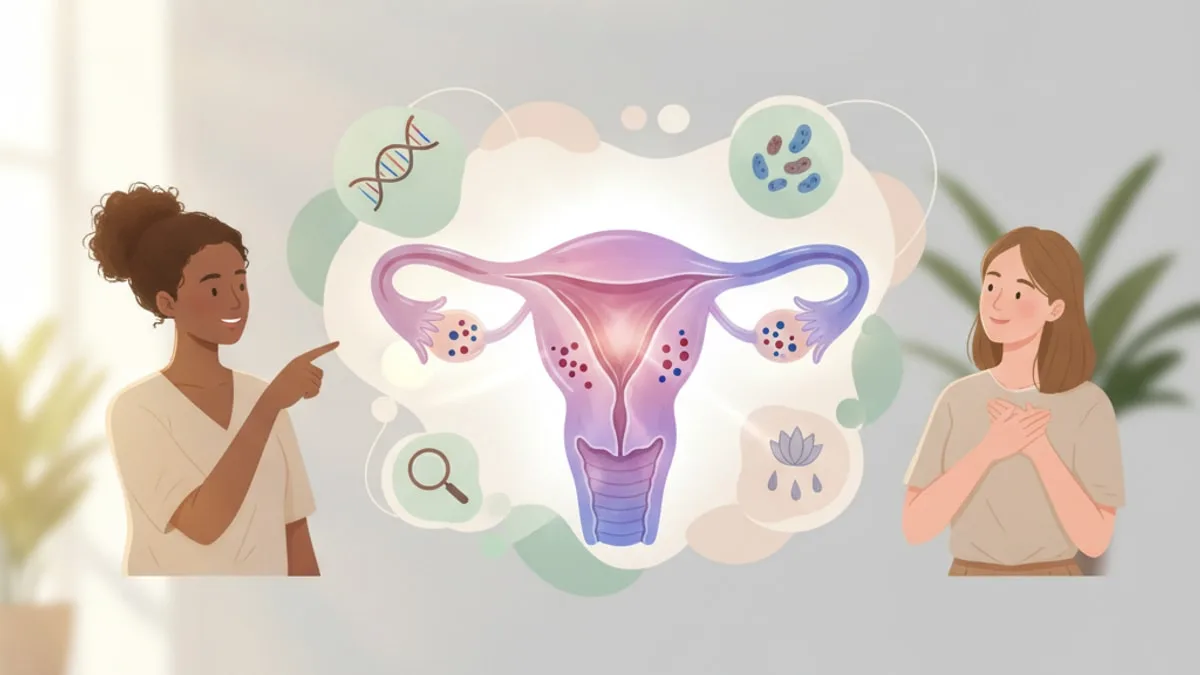
Adenomyosis Symptoms: Signs and Causes
Bleeding that soaks through a pad an hour, or dizziness or fainting with heavy bleeding, means call 911 or go to the emergency department.
The rest of this page covers what can contribute to adenomyosis, what the symptoms can feel like, how clinicians look at the uterus, and the two blood markers worth having on a panel when periods are heavy.
What causes adenomyosis?
Adenomyosis happens when tissue that resembles the lining of the uterus is found within the muscular wall of the uterus, and there is no single trigger that explains why it happens in one person and not another. The causes of adenomyosis are not fully settled, and the factors discussed are background conditions rather than things anyone did wrong.
Reproductive history sits near the front of that list. Research suggests that childbirth, prior surgery involving the uterus and age within the reproductive years are among the factors considered in adenomyosis 1. The shared thread is the boundary between the uterine lining and the muscle beneath it, which can be disturbed by pregnancy, delivery or an instrument passing through the uterus.
Hormonal exposure across the reproductive years is the second thread. The uterine lining responds to estrogen each cycle, and tissue sitting inside the muscle wall responds in a similar way, which is part of why symptoms can track the cycle. A clinical update describes adenomyosis in people of reproductive age and sets out the features reported with it 2.
There is also an overlap with endometriosis. Research suggests that adenomyosis and endometriosis share parts of their underlying biology, including how the tissue behaves and the inflammatory signalling around it 3. That overlap matters in practice, because pelvic pain can have more than one source at the same time.
How widespread adenomyosis is depends on how it is defined and who is being examined. Estimates of how common adenomyosis is vary with the definition used and the group studied 1, and a global review of adenomyosis and endometriosis reports a similar spread across populations 4.
Sleep, stress, training load, alcohol and diet are not the cause of adenomyosis. They are still worth mentioning at an appointment, because they shape how heavy bleeding feels day to day and they overlap with the tiredness that follows repeated blood loss. Some medicines also change how much a person bleeds, so ask your prescriber about anything you take rather than changing it on your own.
None of these factors appears on a blood panel. That is the honest starting point for everything below.
What do the symptoms feel like?
Painful periods, heavy menstrual bleeding, pelvic pressure and an enlarged uterus are the features set out for adenomyosis in a clinical guideline on the condition 5. Those four describe the pattern more accurately than any single symptom does.
The pain can start a day or two before bleeding and can sit deep and low rather than on the surface. Some people describe cramping that builds through the heaviest days, pressure or fullness low in the pelvis, pain with sex, and bleeding that arrives with clots or lasts longer than it used to. Studies indicate that heavy menstrual bleeding and painful periods are among the features reported in adenomyosis 2.
Fertility is a reasonable question to raise early. Adenomyosis is associated with difficulty conceiving and with outcomes during fertility care 6. If you are trying to conceive, or have been trying without success, ask your OB or fertility specialist, who can look at the uterus, your history and your results together.
The awkward part is that this symptom picture is not unique. Heavy, painful periods and pelvic pressure can come from several sources, which is why the next step is looking at the uterus rather than guessing from symptoms alone.
How do clinicians look at the uterus when periods are heavy and painful?
Imaging does the looking, because adenomyosis sits within the muscle of the uterine wall where no blood marker can reach. A clinician starts with your history and an examination, then uses a scan to see the wall itself.
Pelvic ultrasound is the first look. A consensus group has defined the ultrasound features used when the uterine wall is assessed, including a thickened or asymmetric wall, small cysts within the muscle and an unclear border between the lining and the muscle 7. Those features are read together rather than one at a time.
When the ultrasound picture is unclear, or when the pelvis needs a fuller view, MRI can add detail. Research suggests that combining the clinical picture with imaging gives a more complete assessment than either alone 8, and a guideline on adenomyosis sets out how assessment and imaging fit together in practice 5.
A scan report is not a verdict you read alone. A finding on imaging is worth discussing with the clinician who ordered it, and that clinician decides what the picture reflects and what comes next. Treatment decisions belong to a licensed provider.
Which blood tests can help explain the symptoms?
Blood tests do not look at the uterus, but two markers track what heavy bleeding costs the body, and both are standard when someone reports heavy periods.
| Marker | Why it matters when periods are heavy | What a result can and cannot tell you |
|---|---|---|
| Hemoglobin | Hemoglobin carries oxygen inside red blood cells, and repeated blood loss removes red cells faster than they can be replaced. | A value outside the range printed on your lab report is worth discussing with a clinician, who decides what it reflects. It says nothing about the uterine wall and cannot explain why bleeding is heavy. |
| Ferritin | Ferritin reflects stored iron, the reserve the body draws on to keep red cell production going between cycles. | A value outside the printed range is worth raising promptly with a clinician. Ferritin can rise with inflammation, so it is read alongside the rest of the panel rather than alone. |
Compare any value against the range printed on your own lab report, because reference ranges vary by lab, age and sex.
Can heavy periods pull hemoglobin down?
Yes, sustained blood loss can lower hemoglobin over time. Hemoglobin is the iron-containing protein inside red blood cells that carries oxygen from the lungs to the rest of the body. Every period removes red cells. When the volume lost each cycle outpaces the marrow's ability to replace them, the running total drifts down, and the symptoms that follow are tiredness that sleep does not fix, a racing heart with ordinary effort, pale skin and poor exercise tolerance.
The timeline matters more than any single reading. A hemoglobin value taken once is a snapshot. The same value repeated across several months, alongside a record of how heavy your periods have been, tells a clinician far more about the direction of travel.
Several other things move hemoglobin, which is why the number alone settles nothing. Hydration changes plasma volume and can make a reading look higher or lower than the underlying red cell mass. Living at altitude pushes it up. Pregnancy shifts it, and that conversation belongs with your OB or midwife. Kidney function, B12 and folate status, inherited red cell conditions and recent blood donation all change the picture. A clinician reads hemoglobin next to the full blood count, not on its own.
Can ferritin fall before hemoglobin does?
Yes, iron stores can run low while hemoglobin still sits inside the printed range. Ferritin is the protein that holds iron in storage, and its level in blood gives an indirect read on how much iron the body has in reserve. When monthly losses exceed what food and absorption replace, the body draws down stores first and protects red cell production for as long as it can. That is why ferritin can be the earlier signal and hemoglobin the later one.
Low stores can show up as fatigue, breathlessness with stairs, cold hands, hair shedding, restless legs at night or a general sense that recovery from training has slowed. These are non-specific, which is exactly why the marker is worth measuring rather than guessing at.
Ferritin has an important quirk. It also behaves as an acute phase protein, meaning it climbs during inflammation, infection or after intense training, and that rise can sit on top of genuinely low stores and make them look adequate. Liver conditions, alcohol intake, inherited iron overload and recent iron intake all move it too. A clinician reads ferritin with inflammatory markers and the full blood count before deciding what a value reflects, and decides whether anything needs to change.
What can a normal panel still miss?
A normal hemoglobin and a normal ferritin do not rule adenomyosis in or out, because neither marker looks at the uterine wall. This is the central limit of blood testing for this symptom picture.
Several things a blood panel cannot see are the ones that actually explain heavy, painful periods. The structure of the uterine wall sits on imaging, not in serum, and the defined ultrasound features are read from a scan. Endometriosis lesions outside the uterus are not visible on a blood draw either. Scar tissue from earlier surgery, the position and size of the uterus, and how much a period disrupts work, sleep and intimacy are all outside the reach of a panel.
Timing adds another limit. A sample drawn a week after a heavy period looks different from one drawn mid-cycle, and recovery from blood loss takes time. Note where you are in your cycle when blood is taken, so results can be compared fairly next time.
The practical conclusion is simple. Use blood markers to understand the cost of bleeding and to track it, and use imaging and a clinical assessment to understand the uterus.
When should you see a clinician quickly?
Some symptoms need emergency care rather than an appointment. Call 911 or go to the emergency department for any of these.
- Bleeding that soaks through a pad or tampon every hour for more than two hours
- Dizziness or fainting with heavy bleeding
- Chest pain or pressure
- Trouble breathing
- Severe pelvic or abdominal pain that comes on suddenly
A separate set of symptoms calls for a prompt visit, within days rather than months.
- Periods that keep you from work, school, training or sleep
- Pelvic pain between periods, or pain with sex
- A new feeling of pelvic pressure, fullness or swelling that does not settle
- Bleeding between periods, or any bleeding after menopause
- Tiredness that has built up alongside months of heavy bleeding
- Difficulty getting pregnant, which is a question for your OB or fertility specialist
Bring specifics to that visit. How many days you bleed, how fast you soak through protection, clot size, pain scores and any recent lab results give a clinician more to work with than a general description.
This page is educational and is not medical advice. Discuss your symptoms, your results and any treatment with a clinician or licensed provider, who decides what is appropriate for you.
If you are having thoughts of self-harm, call or text 988 (US) or your local emergency number now.
How can you check these markers?
Both markers sit on a standard blood panel, and the FitScript Essential panel includes hemoglobin and ferritin alongside the rest of a baseline workup. Membership testing covers 150+ biomarkers tested per year, so a value can be followed across cycles rather than read once and forgotten.
Results arrive with interpretation. Atlas, FitScript's AI health advisor, explains what each value means in plain language, how it sits against the range printed on your report, and which results are worth raising at your next appointment. A licensed clinician decides on any next step, including whether imaging or a referral makes sense, and any treatment decision belongs to that provider.
If you already have recent bloodwork from another lab, bring those numbers to the same conversation. Older results give context that a single new panel cannot.
Key takeaways
- Adenomyosis is tissue resembling the uterine lining sitting inside the muscular wall of the uterus, and no single cause explains it.
- Painful periods, heavy bleeding, pelvic pressure and an enlarged uterus are the features set out in a clinical guideline 5.
- Blood tests cannot see the uterine wall. Hemoglobin and ferritin track what bleeding has cost the body, and a value outside the printed range is worth discussing with a clinician.
- Ferritin can fall before hemoglobin does, and it rises with inflammation, so it is read alongside the rest of the panel.
- Imaging and a clinical assessment are what a clinician uses to look at the uterus 8, and fertility questions belong with your OB or fertility specialist.
For the wider picture on bleeding volume and on the other growths that share this symptom pattern, see heavy periods causes and fibroids symptoms.
References
- Epidemiology of Adenomyosis. Seminars in Reproductive Medicine, 2020.
- Adenomyosis: An update regarding its diagnosis and clinical features. Journal of Gynecology Obstetrics and Human Reproduction, 2021.
- Endometriosis and adenomyosis: shared pathophysiology. Fertility and Sterility, 2023.
- Global prevalence of adenomyosis and endometriosis: a systematic review and meta-analysis. Reproductive Biology and Endocrinology, 2025.
- Guideline No. 437: Diagnosis and Management of Adenomyosis. Journal of Obstetrics and Gynaecology Canada, 2023.
- Adenomyosis and Infertility: A Literature Review. Medicina, 2023.
- Consensus on revised definitions of Morphological Uterus Sonographic Assessment (MUSA) features of adenomyosis: results of modified Delphi procedure. Ultrasound in Obstetrics & Gynecology, 2022.
- Diagnosing adenomyosis: an integrated clinical and imaging approach. Human Reproduction Update, 2020.
Common questions
Adenomyosis versus fibroid, what is the difference?
Adenomyosis is tissue like the uterine lining sitting within the muscular wall of the uterus, so the wall itself thickens and the border blurs. A fibroid is a separate growth of muscle and fibrous tissue with a defined edge on a scan. Both can produce heavy, painful periods, and both can be present at once. Imaging and a clinician sort them out.
Can a blood test show adenomyosis?
No. Adenomyosis sits inside the muscle of the uterine wall, and no blood marker reaches there. Blood tests do something different, which is tracking what heavy bleeding costs the body through markers such as hemoglobin and ferritin. A pelvic scan and a clinical assessment are what a clinician uses, and that clinician decides what the picture reflects.
Why would a clinician check hemoglobin and ferritin when periods are heavy?
Because both reflect the cost of repeated blood loss. Hemoglobin carries oxygen in red blood cells, and ferritin reflects stored iron the body draws on to replace them. Ferritin can fall while hemoglobin still sits inside the printed range. A value outside your report's range is worth discussing with a clinician, who decides what it reflects.
Does adenomyosis change around menopause?
Hormone patterns shift around menopause, and symptoms can change with them. How that plays out varies from person to person, so there is no single timeline anyone can promise you. If pelvic pain or heavy bleeding continues, or if any bleeding starts after menopause, book a prompt visit and let a clinician assess it.
Can adenomyosis affect getting pregnant?
It can be relevant to fertility and to pregnancy care, and the picture varies a great deal between individuals. If you are trying to conceive, or have been trying without success, ask your OB or fertility specialist. They can look at the uterus, your cycle history and your bloodwork together before suggesting any next step.
What does a pelvic ultrasound look for?
It looks at the size, shape and texture of the uterine wall. The features a sonographer notes include a thickened or uneven wall, small cysts within the muscle and an unclear border between the lining and the muscle beneath it. A clinician reads those features alongside your symptoms and decides whether a further scan adds anything.
Can adenomyosis and endometriosis happen together?
Yes, both can be present in the same person, and their symptoms overlap enough that one can mask the other. Pain with periods, pain with sex and pelvic pain between periods can belong to either. Describe the full pattern across a few cycles to your clinician rather than just the single worst day.
What should I bring to an appointment about heavy, painful periods?
Bring a record of your cycle covering how many days you bleed, how quickly you soak through protection, clot size, pain scores and what the pain stops you doing. Add any recent lab results and a list of medicines you take, and ask your prescriber about anything that might affect bleeding.